Points clés à retenir
- MSP codes reflect care complexity and timing: BC emergency medicine billing uses three care levels, with different fee codes depending on when care begins.
- Shadow billing makes clinical work visible: Physicians working under alternative payment arrangements may need to submit patient-level encounter information.
- Consistent billing protects accuracy: Recording care times, documenting medical necessity, identifying the correct payment arrangement, and reviewing submissions help prevent errors and underreported activity.
Emergency medicine billing in British Columbia requires physicians to navigate more than a list of MSP fee codes. Patient complexity, time of care, documentation requirements, and compensation arrangements all influence how clinical services should be recorded and submitted.
For physicians working under fee-for-service (FFS), accurate billing helps ensure eligible services are compensated appropriately.
For those working under alternative payment arrangements, shadow billing and encounter reporting remain important even when individual claims don’t generate direct payment.
This guide explains the key BC emergency medicine billing rules, how shadow billing fits into alternative payments, and practical ways to avoid common mistakes.
Understanding emergency medicine billing in British Columbia
There are two ways emergency physicians in BC typically receive compensation: fee-for-service or alternative payment arrangements.
- Under traditional FFS, physicians submit eligible claims to the Medical Services Plan (MSP) based on services provided. Payment depends on the applicable fee schedule and billing requirements.
- Under alternative arrangements, physicians may receive compensation through contracts rather than individual claim payments. However, clinical activity may still need to be reported through MSP’s Teleplan system.
Importantly, the Emergency Medicine section of the MSC Payment Schedule applies to designated emergency physicians working on-site in eligible hospital emergency departments. However, not all facilities providing emergency care use these fee codes.
At some facilities, physicians must use out-of-office visit codes, with applicable evening, night, or weekend premiums. Physicians providing call-in coverage or attending their own patients in the ED may also need to use different fee schedules.
Confirm your facility’s billing designation and applicable fee schedule before submitting claims.
Understanding which arrangement applies is the first step toward accurate billing.
BC emergency medicine MSP codes: Understanding care levels
BC’s emergency medicine fee schedule categorizes eligible patient encounters into three levels based on the complexity of care provided.
Level I: Straightforward conditions
Level I generally applies to a single, uncomplicated condition requiring a focused assessment and treatment.
Exemples: Uncomplicated urinary tract infections, localized skin conditions without systemic symptoms, and certain minor joint injuries.
Level II: More detailed assessment
Level II applies when a medical condition requires a more detailed history, examination, investigation, or treatment.
Exemples: Concussions, head injuries involving anticoagulants, and conditions requiring additional clinical evaluation.
Level III: Serious or complex conditions
Level III applies to serious or complex presentations requiring comprehensive assessment and potentially prolonged observation, ongoing treatment, or multiple reassessments.
Exemples: Severe illness requiring extensive investigation, complex multi-system presentations, or life-threatening conditions that don’t meet resuscitation fee criteria.
The documented clinical work determines the appropriate level, not the diagnosis alone.
BC emergency medicine fee code reference
Care level | Weekday daytime | Weekday evening | Night | Weekend/holiday |
Level I | 01811 | 01821 | 01831 | 01841 |
Level II | 01812 | 01822 | 01832 | 01842 |
Level III | 01813 | 01823 | 01833 | 01843 |
The applicable billing periods are:
- Daytime: Weekdays, 8 a.m. to 6 p.m.
- Evening: Weekdays, 6 p.m. to 11 p.m.
- Night: 11 p.m. to 8 a.m.
- Weekend/statutory holiday: 8 a.m. to 11 p.m.
The billing category depends on when the physician starts care. This includes reviewing the patient’s chart before direct interaction.
Triage and registration times don’t determine the applicable fee.
Example: a physician beginning documented care at 10:55 p.m. on a weekday generally uses the evening category, even if treatment continues after 11 p.m.
What’s shadow billing in BC emergency medicine?
Shadow billing is the process of recording clinical services that don’t generate conventional fee-for-service compensation because the physician is paid through another arrangement.
Instead of using claims primarily to trigger payment, encounter reporting captures the clinical activity performed.
- For BC Alternative Payment Arrangements (APAs), provincial guidance requires patient-level encounter reporting through Teleplan for clinical services delivered under the contract. This means that documentation is essential.
Consider an emergency physician working a contracted hospital shift. They assess 20 patients, including several complex cases requiring additional investigation and treatment.
Their compensation may remain fixed regardless of the individual MSP fees associated with those encounters. However, submitting complete encounter records ensures the work performed is represented in provincial administrative data. This is how funding, resources, and planning needs are assessed.
The precise coding, submission, and reconciliation requirements depend on the physician’s agreement and applicable reporting instructions.
For a broader overview, read Petal’s Shadow billing explained: What it is, how it works, and why it matters.
What happens when a patient isn't covered by MSP?
Even when physicians work under an Alternative Payment Arrangement, not every encounter follows the standard $0.00 shadow billing process.
For patients without valid MSP coverage, or whose services are payable through another program, billing teams may need to convert encounter codes into fee-for-service equivalents.
Keep in mind that while encounter reporting may require only one applicable code per visit, FFS recovery can involve multiple eligible fee codes for the same encounter. This depends on factors like services provided, documentation, and relevant billing rules.
- Examples include patients covered by WorkSafeBC (WCB), certain out-of-province patients, Department of National Defence (DND) beneficiaries, and patients eligible under the Interim Federal Health Program (IFHP).
You could manage your shadow billing… or Petal’s BC-based experts could.
Additional emergency medicine billing codes to understand
Beyond the three emergency care levels, several MSP codes address specific circumstances.
MSP code | Service | Key consideration |
01810 | Emergency medicine consultation | Specific referral and physician qualification rules apply. |
01870 | Emergency medicine resuscitation | Requires constant bedside care for qualifying emergencies. |
P01882 | Emergency medicine reassessment | Additional medically necessary reassessment must satisfy timing criteria. |
P01880 | Specialist patient management/follow-up | Applies to eligible urgent verbal follow-up communications. |
P01881 | Emergent telehealth advice | Available to eligible emergency physicians providing requested advice. |
Example: Resuscitation code 01870 is billed in five-minute units or portions thereof for qualifying care. Start and end times must be documented, and certain procedures central to resuscitation are included.
Likewise, P01882 has specific reassessment intervals. Reviewing test results alone doesn’t establish eligibility.
Physicians should confirm whether these services are separately payable under their compensation arrangement or require encounter reporting instead.
6 Common BC emergency medicine billing mistakes
Several recurring workflow risks deserve attention:
1. Selecting an incorrect care level
A complex diagnosis doesn’t automatically justify a Level III fee. Documentation must support the applicable complexity criteria.
2. Using the wrong start time
Using registration time instead of the documented beginning of physician care can result in an incorrect time-based code.
3. Missing encounters under alternative payment arrangements
When physicians assume non-FFS claims are unnecessary, clinical activity may go unreported.
4. Confusing contracted and FFS services
Submitting an FFS claim for services already covered by a contract may cause ineligible or duplicate claims. Conversely, failing to identify encounters involving patients without valid MSP coverage or those covered by third-party payers leads to missed billing opportunities.
5. Insufficient reassessment documentation
Additional visits require evidence of medical necessity. Routine observation or reviewing investigations may not qualify.
6. Overlooking billing reconciliation
Without reviewing submitted and accepted records, physicians and billing teams may miss rejected claims, reporting gaps, or incorrectly classified encounters.
These issues demonstrate why billing accuracy depends on both clinical documentation and a consistent administrative process.
Emergency medicine billing checklist
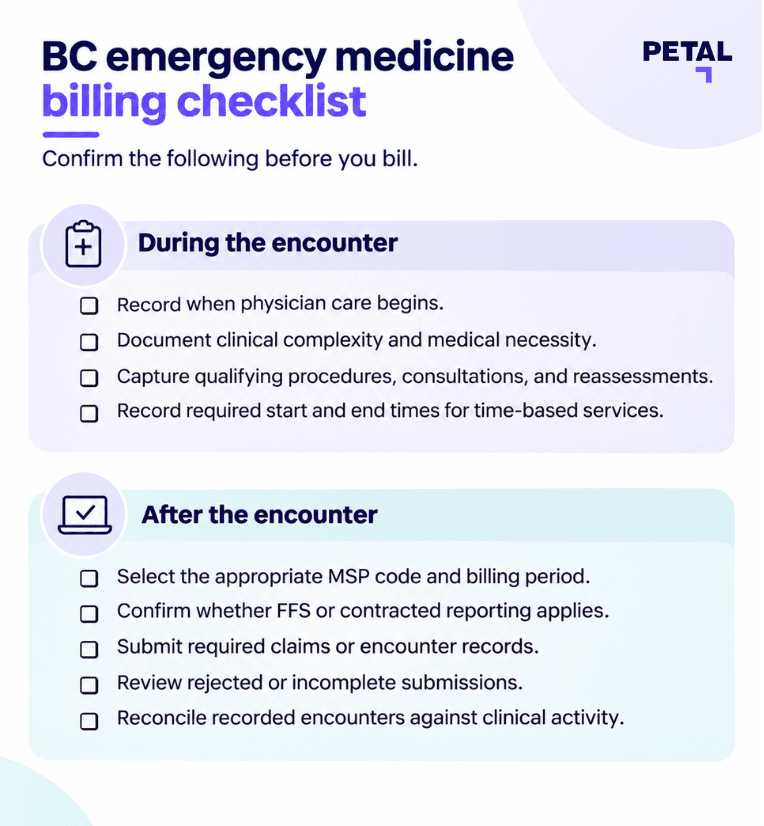
Before completing a shift’s billing, physicians and billing teams should confirm the following:
During the encounter
- Record when physician care begins.
- Document clinical complexity and medical necessity.
- Capture qualifying procedures, consultations, and reassessments.
- Record required start and end times for time-based services.
After the encounter
- Select the appropriate MSP code and billing period.
- Confirm whether FFS or contracted reporting applies.
- Submit required claims or encounter records.
- Review rejected or incomplete submissions.
- Reconcile recorded encounters against clinical activity.
A consistent workflow helps reduce administrative follow-up while improving the reliability of submitted data.
Accurate billing makes emergency care visible
Emergency medicine billing in BC serves two important purposes: supporting appropriate payment for eligible services and accurately recording clinical care under alternative compensation arrangements.
Whether physicians submit traditional FFS claims or shadow-billed encounters, accurate reporting helps reduce administrative problems and improve visibility into the work performed.
As compensation arrangements evolve, reliable billing processes become increasingly important for physicians and healthcare organizations.
Petal Medical Billing BC helps physicians manage complex billing workflows, reduce administrative work, and maintain accurate claims and reporting.
FAQs: BC emergency medicine billing and codes
What MSP codes do BC emergency physicians use?
Designated on-site emergency physicians generally use Level I, II, and III emergency care codes, with different codes for daytime, evening, night, and weekend or statutory holiday services. Additional codes cover eligible consultations, resuscitations, and reassessments.
Is shadow billing required for emergency physicians in BC?
Patient-level Teleplan encounter reporting is required for clinical services covered by BC Alternative Payment Arrangements. Other compensation models may have different reporting requirements, so physicians should confirm their agreement.
Can emergency physicians bill for reassessments?
Yes, when the relevant MSP criteria are satisfied. Code P01882 includes specified minimum intervals and requires documentation explaining the medical necessity of the additional visit.
How can emergency physicians avoid billing errors?
Accurate documentation, appropriate code selection, correct compensation classification, timely submission, and regular reconciliation help reduce errors and incomplete reporting.